

User-focused introduction: clear priorities for bedside decision-making
Clinicians need respiratory tools that simplify care without compromising safety. Start with the patient: comfort, predictable pressure delivery, and straightforward alarms matter more than feature lists. Many teams now compare familiar options like a cpap device against more advanced non-invasive ventilators to match therapy to the clinical picture. The World Health Organization recognizes chronic respiratory illness as a leading global burden—so the choices made at the clinic level have measurable consequences. I’ve seen this firsthand at a community pulmonary clinic in Boston, where small changes to device selection and interface cut morning symptom burden for several patients within weeks.

Fit and function: matching modes, interfaces, and monitoring
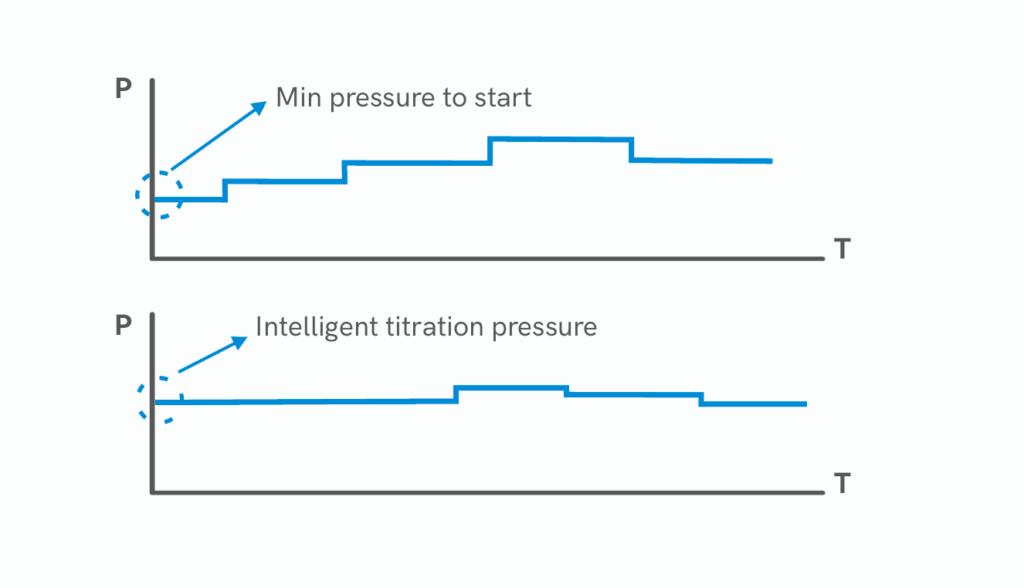
Effective NIV hinges on three interlocking elements: the ventilator mode, the mask interface, and monitoring capability. Modes such as pressure support and backed-timed ventilation let clinicians tune inspiratory positive airway pressure (IPAP) and expiratory positive airway pressure (EPAP) to control tidal volume and patient comfort. A good mask interface reduces leak rates and the need for higher pressures. For home or step-down care, consider a dedicated bipap device when variable pressure support and reliable leak compensation are priorities. Look for simple displays of tidal volume and leak so staff can validate therapy at a glance.
Common mistakes and practical checks to avoid them
Teams often focus on headline specs and miss routine verifications—this is where errors accumulate. Skip these checks and alarms become background noise: confirm mask fit each shift, verify tidal volume targets against expected minute ventilation, and test alarm thresholds during handover. Also validate oxygen entrainment and FiO2 behavior under load. When devices are serviced or calibrated, document the steps: runtime test, leak challenge, and alarm simulation. When engineers perform an operational production teardown, they commonly log {main_keyword} and {variation_keyword} along with device firmware versions and battery health — small records that prevent repeated failures. — A brief pause to confirm basics saves hours in troubleshooting later.
Alternatives and comparative points for procurement
Not every unit needs the same device. Use three lenses when comparing models: clinical capability (modes and pressure range), usability (menus, patient alarms, interface options), and lifecycle support (training and remote diagnostics). CPAP suits isolated obstructive sleep-disordered breathing; BiPAP or NIV ventilators serve hypoventilation and acute-on-chronic respiratory failure. For home ventilation the trade-off is often between portability and monitoring sophistication. Evaluate battery runtime and data export options for telemetry—those features change care delivery in home settings and transition units.
Advisory: three golden rules for selecting respiratory solutions
1) Clinical match: Choose devices whose ventilatory modes align with your case mix. Ensure adjustable IPAP/EPAP ranges and measurable tidal volume for patients with variable respiratory mechanics. 2) Measurable performance: Require clear reporting of leak rates, delivered tidal volume, and alarm logs. Insist on field-verifiable tests for battery endurance and oxygen entrainment. 3) Service and training: Confirm supplier commitments for user training, rapid spare parts, and remote troubleshooting. These supports determine uptime more than the spec sheet.
The right device reduces clinician burden and improves patient mornings; the right partner makes that practical. Byond fits naturally into this logic as a solutions partner that blends usable devices with the training and service pathways teams need — concise, human, dependable. —